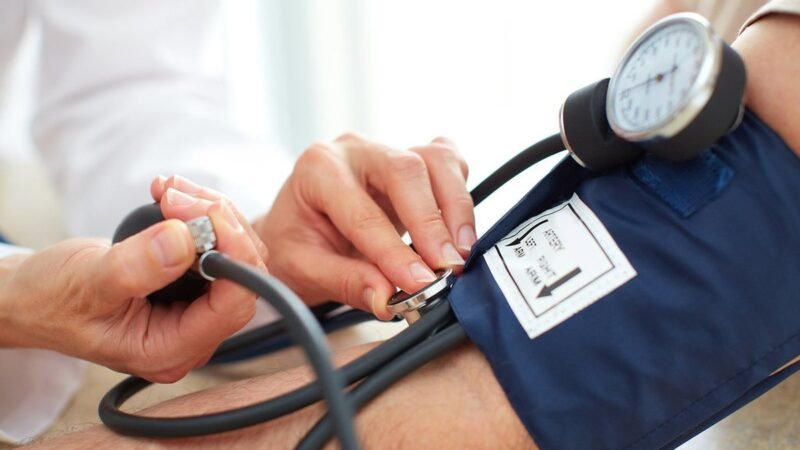
Blood pressure is the force of blood against artery walls, written as two numbers such as 120/80 and measured in millimetres of mercury. The top number, systolic, is the pressure during a heartbeat. The bottom number, diastolic, is the pressure while the heart rests between beats. Both matter, and guidelines group readings into categories to guide monitoring and treatment decisions.
The commonly used categories
Under widely used American guidelines, normal is below 120/80; elevated is systolic 120 to 129 with diastolic under 80; stage 1 hypertension begins at 130/80, and stage 2 at 140/90. European guidelines use somewhat different thresholds, often treating 140/90 as the hypertension line, which is exactly why your own clinician’s framework — not an article — decides what your number means for you.
Why one reading is not a verdict
- Cuff size, posture, a full bladder, caffeine, talking during measurement and recent exercise all move readings.
- White-coat effect raises readings in clinics for many people; home readings over several days give clinicians a truer average.
- Proper technique: sit quietly five minutes, back supported, feet flat, arm supported at heart level, correct cuff size, no talking.
What the evidence does not prove
A single high reading does not diagnose hypertension, and a single normal one does not clear it; patterns over time do. Lifestyle measures — activity, weight, salt reduction, limiting alcohol, not smoking — are genuinely supported for helping blood pressure, but they are complements to medical care, not substitutes when medication is prescribed. Never adjust blood pressure medication based on home readings without your clinician.
If you monitor at home, bring the device and a week of morning and evening readings to your appointment. That log is more valuable than any single number, including the one that worried you into searching.